

Introduction
Lead poisoning shouldn't still be a problem in 2025. Leaded gasoline is gone. Lead paint has been banned since 1978. Yet lead exposure remains one of the most common preventable environmental health threats in the United States, still harming children and adults through old paint dust, contaminated soil, and aging pipes.
The real danger is that lead poisoning is often silent. Many people with elevated blood lead levels feel completely fine, until the damage to the brain, kidneys, or developing nervous system has already begun. That's why routine screening matters so much.
This guide walks through how doctors diagnose lead poisoning, what treatments like chelation therapy do, and which supportive steps protect long-term health once care is underway.
Key Takeaways
- Remove the exposure source first: no medication works while exposure continues
- Chelation therapy is reserved for higher blood lead levels or symptomatic cases—and never used alone
- Children face stricter thresholds than adults because of developmental vulnerability
- Calcium, iron, and vitamin C intake can reduce lead absorption
- Long-term follow-up is essential: blood lead levels can rebound after treatment
Understanding Lead Poisoning: Causes and Symptoms
Lead doesn't announce itself. It builds up quietly through everyday contact with contaminated dust, water, or products.
The most common sources include:
- Deteriorating lead-based paint and dust in homes built before 1978
- Contaminated soil near old buildings or roadways
- Corroding lead pipes and plumbing fixtures
- Imported ceramics, cosmetics, candies, toys, or traditional remedies
- Take-home dust from occupational exposure (construction, battery recycling, radiator repair)
Symptoms Differ by Age
Children and adults show different warning signs, and both groups can have no symptoms at all despite elevated levels.
In children, watch for:
- Fatigue and low energy
- Abdominal pain and poor appetite
- Irritability or behavioral changes
- Learning difficulties or developmental delays
- Anemia
In adults, common signs include:
- Headaches and memory problems
- Joint and muscle pain
- High blood pressure
- Reproductive issues, including reduced fertility
- Abdominal cramping or constipation
Most cases are asymptomatic, so waiting for symptoms before testing means waiting too long. The CDC recommends routine screening for:
- Children under 6
- Pregnant women with risk factors
- Workers in lead-related industries
Diagnosing Lead Poisoning
Diagnosis starts, and often ends, with a simple blood test.
The standard process:
- Capillary screening — a quick finger-prick or heel-prick test, typically used for initial screening
- Venous confirmation — required for any elevated capillary result, since finger-prick tests can produce false positives
- Follow-up testing — timing depends on the initial result
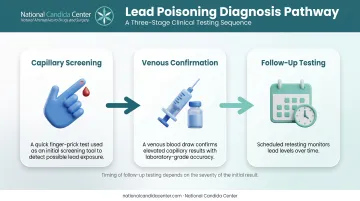
Confirmation timelines matter:
- 3.5–9 µg/dL — confirm within three months
- 10–19 µg/dL — confirm within one month
- 20–44 µg/dL — confirm within two weeks
- 45 µg/dL or higher — confirm within 48 hours
There's an important nuance most people miss: there's no truly "safe" blood lead level. The CDC's current blood lead reference value sits at 3.5 µg/dL, a threshold used to flag children with levels higher than most of their peers, not a marker of safety. Levels of 45 µg/dL or above in children typically trigger active medical intervention.
Supplementary testing often includes:
- Iron deficiency and anemia screening (iron-deficient children absorb lead more readily)
- Abdominal X-rays, to check for ingested paint chips or lead objects
- Developmental milestone checks in young children
Results from these tests shape urgency and whether chelation or other medical intervention is warranted.
Lead Poisoning Treatment: How Chelation Therapy Works
For significant lead poisoning, the standard medical treatment is chelation therapy combined with mandatory removal from the exposure source. Neither works well without the other. Chelation without source removal just sets up a rebound.
Chelating agents work by binding to lead circulating in the bloodstream, forming a compound the body can excrete through urine instead of storing it in soft tissue and bone.
The Three Main Chelating Agents
| Agent | Used For | Key Safety Note |
|---|---|---|
| Succimer (DMSA) | Oral, first-line for children with BLLs above 45 µg/dL without encephalopathy | Requires weekly blood counts and liver enzyme monitoring |
| CaNa₂EDTA | Injectable, moderate-to-severe cases | Must never be confused with plain disodium EDTA; that error has caused fatal hypocalcemia |
| Dimercaprol (BAL) | First-line for lead encephalopathy, paired with CaNa₂EDTA at BLLs above 100 µg/dL | Contraindicated with liver problems; can cause injection-site pain and blood pressure spikes |
Dosing and handling differ for each agent:
- Succimer is typically dosed for a 19-day course
- CaNa₂EDTA requires careful fluid management to protect the kidneys
- BAL is reserved for the most severe presentations and is almost always given with CaNa₂EDTA, not alone
A critical warning: CaNa₂EDTA and disodium EDTA are not interchangeable. The CDC has documented hypocalcemia-related cardiac arrest deaths tied to this exact mix-up, including cases involving children.
Chelation isn't a cure. It lowers circulating blood lead, but it does not reverse neurological damage that has already occurred. Lead stored in bone can redistribute into the bloodstream after treatment stops, which is why rebound testing matters as much as the initial course.
Treatment Guidelines by Blood Lead Level: Children vs. Adults
Treatment thresholds aren't the same for kids and adults, and that gap exists for a reason: developing brains are far more vulnerable to lead's effects than mature ones.
Pediatric Action Thresholds
| Blood Lead Level | Recommended Action |
|---|---|
| 3.5–19 µg/dL | Identify and remove sources, evaluate iron status, monitor development |
| 20–44 µg/dL | Add full history/exam, environmental hazard reduction, possible imaging |
| 45–69 µg/dL | Neurologic exam, chelation consultation, prompt admission if symptomatic |
| ≥70 µg/dL or encephalopathy | Medical emergency: hospitalization and combination chelation |
Adult Action Thresholds
| Blood Lead Level | Recommended Action |
|---|---|
| 10–29 µg/dL | Exposure counseling, increased monitoring, possible removal |
| 30–49 µg/dL | Mandatory removal from exposure, prompt evaluation |
| 50–79 µg/dL | Removal, chelation considered with toxicity symptoms |
| ≥80 µg/dL | Immediate removal and urgent evaluation, chelation likely |
Occupational standards set separate workplace triggers. OSHA sets a permissible exposure limit of 50 µg/m³ in air and requires worker removal at a single BLL of 60 µg/dL, or an average of 50 µg/dL across the last three tests.
Lead encephalopathy, regardless of age, is a medical emergency requiring hospitalization, seizure management with IV benzodiazepines, and combination BAL/CaNa₂EDTA chelation.
Those emergency protocols still matter because exposure never fully went away. Among U.S. children ages 1–5, geometric-mean blood lead levels dropped 94.5%, from 15.2 µg/dL in 1976–1980 to 0.8 µg/dL in 2011–2016. Lead paint and gasoline bans drove that decline. They did not erase residual sources.
Supporting Recovery: Nutrition, Prevention, and Long-Term Monitoring
Medical treatment addresses the acute problem. What happens around it, nutritionally and environmentally, shapes long-term outcomes.
Nutrition's Supportive Role
Diets adequate in calcium, iron, and vitamin C can reduce how much lead the gut absorbs. Calcium in particular appears to limit how much lead already stored in bone gets remobilized into the bloodstream. One randomized trial of pregnant women found calcium supplementation associated with an 11% reduction in blood lead levels.
Iron status deserves specific attention. Iron-deficient children absorb lead more readily than iron-replete children, which is why correcting anemia is a genuine adjunct to medical treatment.
Once physician-directed care is in place, functional testing and nutritional support can complement that plan. They do not replace it.
Clinics such as the National Candida Center in Sanford, Florida, work with clients nationwide through remote consultations. They assess toxic metal burden with biological sample testing—urine, blood, feces, and hair—with hair analysis often used as a simple, low-cost first step.
Their Start Up/Alkalize phase (typically 3–5 weeks) pairs dietary coaching with foundational supplements such as Mind-Body Essential Minerals or NitroGreens while lab results are pending. These products support general nutrition and elimination needs; they are not chelating agents.

Anyone with a confirmed elevated blood lead level should use this kind of supportive care alongside chelation therapy prescribed by a physician, not instead of it.
Prevention and Long-Term Follow-Up
- Lead paint: Use only EPA-certified renovators for work disturbing paint in pre-1978 housing
- Water systems: Support corrosion control measures; at home, flush stagnant water and use cold water for cooking and drinking
- Consumer products: Avoid recalled or suspect imported ceramics, toys, jewelry, and cosmetics
After chelation, plan for structured follow-up:
- Recheck blood lead levels when the treatment course ends, then weekly until levels stabilize (rebound is common)
- Maintain developmental surveillance in children
- Monitor renal and hepatic function throughout CaNa₂EDTA treatment
Frequently Asked Questions
What is the most common treatment for lead poisoning?
Removal from the lead source combined with chelation therapy (oral succimer or intravenous EDTA/BAL, depending on severity) is the standard approach. Chelation only works when exposure is also eliminated.
What are the symptoms of excess lead exposure?
Symptoms vary by age and severity, ranging from fatigue, irritability, and abdominal pain to seizures, developmental delays in children, and memory or fertility issues in adults. Many cases show no symptoms at all.
Can lead poisoning be cured or reversed?
Chelation therapy lowers blood lead levels, but existing neurological or organ damage generally isn't reversible. Early detection and prevention matter most because of that limit.
How long does chelation therapy typically take to work?
Blood lead levels are usually rechecked 7–21 days after starting treatment, though full monitoring can extend over several weeks depending on severity and whether rebound occurs.
What foods help reduce lead absorption in the body?
Diets rich in calcium, iron, and vitamin C are linked to lower lead absorption. Nutrition is supportive care alongside medical treatment, not a replacement for it.
Is lead poisoning permanent in children?
Treatment can lower blood lead levels, but associated learning, behavioral, or cognitive effects can persist long-term. Prevention and early screening remain more effective than waiting to treat after damage appears.


