

Introduction
You know the routine: the bloating that shows up by mid-afternoon, the straining that leaves you frustrated, the dull ache that only lets go once you've finally had a bowel movement. If this sounds familiar, you're far from alone.
Among people diagnosed with IBS under the current Rome IV criteria, the constipation-predominant subtype (IBS-C) makes up roughly 34.5% of cases in a large 2023 US survey of over 4,000 patients. That share nearly matches IBS with mixed symptoms and outpaces diarrhea-predominant IBS, per Gastroenterology's 2023 Rome IV prevalence study.
This article walks through conventional medical treatments, practical diet and lifestyle strategies, and a root-cause natural approach that looks beyond symptom control for longer-lasting relief.
Key Takeaways
- IBS-C is chronic but manageable; symptoms can improve dramatically even without a universal cure
- Effective care blends diet changes, medication, and lifestyle habits
- Conventional treatments often ease constipation and pain, not the imbalances behind them
- Functional medicine can uncover drivers like gut dysbiosis for deeper, longer-lasting relief
What Is IBS-C? Understanding the Condition
IBS-C is the constipation-predominant subtype of irritable bowel syndrome. Under the Rome IV criteria, a diagnosis requires recurrent abdominal pain at least one day per week for three months, linked to changes in stool frequency or form.
What separates IBS-C from other subtypes comes down to stool type on abnormal-bowel-movement days:
- IBS-C: More than 25% hard, lumpy stools (Bristol types 1-2), less than 25% loose stools
- IBS-D: The reverse pattern: mostly loose or watery stools
- IBS-M: A mix, with more than 25% of both hard and loose stool types
Common Symptoms of IBS-C
Most people with IBS-C recognize this cluster:
- Infrequent bowel movements
- Hard or lumpy stools that are difficult to pass
- Straining during bowel movements
- Bloating and visible abdominal distension
- Cramping or pain tied to bowel habits that may not fully ease after a bowel movement
Underlying Causes and Risk Factors
IBS-C rarely has one single cause. Instead, several factors tend to overlap:
- Gut-brain axis dysfunction: miscommunication between the gut and nervous system affects motility and pain sensitivity
- Slowed gut motility: waste moves through the colon too slowly, allowing more water absorption and harder stools
- Food sensitivities: certain foods can trigger bloating or altered bowel habits in susceptible individuals
- Chronic stress: heightens visceral sensitivity and disrupts normal digestive rhythm
- Microbiome imbalances: altered gut bacteria and higher methane production are linked to constipation severity
Conventional Treatment Options for IBS-C
Medical management usually starts simple and escalates only when needed. Most clinicians begin with diet and lifestyle changes, move to over-the-counter remedies, then add prescription medication if symptoms persist.
That stepped approach aligns with the American Gastroenterological Association's (AGA) 2022 clinical guidance.
Over-the-Counter (OTC) Approaches
Two OTC options dominate first-line care:
- Fiber supplements: Psyllium softens stool and steadies transit. Research shows modest global IBS benefit, with a number-needed-to-treat of 7 per a dietary fiber review in PMC.
- Osmotic laxatives: Polyethylene glycol (PEG) draws water into the colon and improves stool frequency, but trials show little effect on abdominal pain.
That gap matters. Many IBS-C patients need something that addresses pain too, not just stool frequency.
Prescription Medications
When OTC options fall short, doctors typically turn to one of several FDA-approved drugs:
| Medication | How It Works |
|---|---|
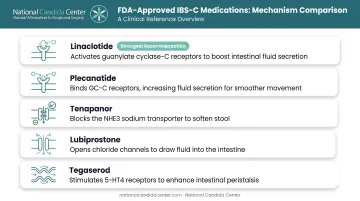
| Linaclotide | Activates gut receptors to boost fluid secretion and speed transit; may also ease pain signaling |
| Plecanatide | Similar to linaclotide: increases intestinal fluid and accelerates movement |
| Tenapanor | Blocks sodium absorption in the gut, pulling more water into the colon |
| Lubiprostone | Activates chloride channels to trigger fluid secretion (approved for women 18+) |
| Tegaserod | Stimulates the gut's natural peristaltic reflex (restricted to women under 65 without cardiovascular risk) |
Linaclotide carries the AGA's strongest recommendation, backed by high-certainty evidence. The FDA even expanded its approval to children age 7 and older in November 2025.
For pain specifically, doctors sometimes add tricyclic antidepressants or antispasmodics. The AGA advises against SSRIs for IBS-C, since trials haven't shown they meaningfully improve symptoms.
These medications manage symptoms only while you take them. They don't resolve the digestive imbalance driving the constipation in the first place.
Diet and Lifestyle Strategies That Support IBS-C Relief
Diet and lifestyle changes are first-line therapy for IBS-C, not a stopgap before medication. Consistent habits can reduce symptoms over months of steady practice.
Fiber and Hydration
Not all fiber behaves the same way in an IBS-C gut:
- Soluble fiber (oats, flaxseed, psyllium) dissolves into a gel and is generally well tolerated
- Insoluble fiber (wheat bran, raw vegetable skins) can worsen bloating and gas for some people with IBS-C
Add fiber gradually, about 2-3 grams per day, so your gut can adjust. Water matters too: fiber needs enough fluid to work, or it can make constipation worse instead of better.
The Low FODMAP Approach
FODMAPs are fermentable carbohydrates (found in foods like onions, garlic, wheat, and certain fruits) that can trigger gas, bloating, and altered bowel habits in sensitive individuals.
A dietitian-guided low FODMAP elimination, typically lasting 2-6 weeks, helps identify your personal trigger foods before a structured reintroduction phase. According to Monash University's FODMAP research team, roughly 3 out of 4 people with IBS report symptom improvement on this approach.
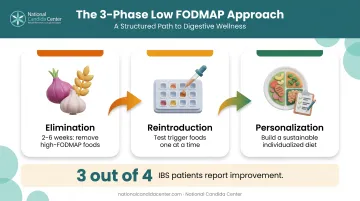
This isn't meant to be permanent. Use it as a diagnostic tool: restrict, learn, then personalize.
Lifestyle Factors
Beyond food, daily habits shape how your gut behaves:
- Regular exercise: a 12-week activity program reduced constipation symptoms in IBS patients
- Consistent meal timing: eating at similar times each day supports a predictable digestive rhythm
- Stress reduction: yoga, meditation, and CBT can ease symptoms tied to the gut-brain connection
Beyond Symptom Management: A Root-Cause, Natural Approach to IBS-C
Here's the limitation nobody talks about enough: fiber, laxatives, and prescription drugs target constipation and pain. They rarely ask why your gut stopped functioning normally in the first place.
Three overlapping contributors often sit underneath IBS-C symptoms, and conventional care frequently misses them:
- Candida yeast overgrowth — when yeast that normally lives in balance with healthy gut flora multiplies unchecked
- Leaky gut — increased intestinal permeability that can trigger inflammation and immune reactivity
- Gut dysbiosis — a broader disruption of the microbial ecosystem that regulates digestion, motility, and even mood
Functional medicine lab testing can show which of these imbalances is actually present instead of treating IBS-C as a one-size-fits-all label. That usually means three-day stool cultures, microbial sensitivity panels, and food sensitivity testing for IgA, IgG, and IgE markers.
National Candida Center, a holistic practice based in Sanford, Florida, has spent over 30 years treating IBS, leaky gut, and Candida-related digestive disorders through individualized testing. Its 5 Phase Treatment Plan (Alkalize, Replace, Reinoculate, Repair, and Remove) walks patients through a sequential process:
- Alkalize (about 3–5 weeks): diet coaching, initial supplements, and baseline testing for inner ecology, food allergies, or toxic metals
- Replace: restore digestive enzymes and support normal digestive function
- Reinoculate: rebuild beneficial flora with targeted prebiotics and probiotics
- Repair: support the intestinal lining with focused nutrients
- Remove (4–12 weeks): elimination diet plus herbal botanicals matched to stool-sensitivity results, aimed at yeast, bacteria, or parasites driving dysbiosis
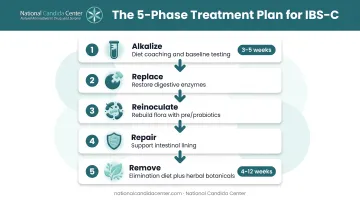
This structure feeds into the Center's broader Healthy Trinity Treatment Strategy: diet (guided by testing, not guesswork), targeted therapy through the 5-phase framework, and mind-body support for stress, sleep, and lifestyle patterns that influence gut function.
Supplements used in-protocol include Mind-Body-Biome Prebiotics/Probiotics (Reinoculate phase) and Candisol, an enzyme blend for Candida-related dysbiosis. Both are sourced with FDA-certified quality assurance.
That quality bar matters. A 2015 New York Attorney General investigation found that 80% of tested supplements did not contain what their labels claimed. Patients also get access to Xymogen, Metagenics, and Designs for Health, all assay-tested for accuracy and contamination.
If you've tried fiber, laxatives, and prescription medication with only partial or temporary relief, a root-cause evaluation is the logical next step—not another round of temporary symptom control.
When to See a Doctor
Most IBS-C is manageable without emergency care, but certain symptoms need prompt medical evaluation:
- Rectal bleeding or black, tarry stool
- Unintended weight loss
- New symptom onset after age 50
- Fever, chills, or night sweats
- Symptoms that wake you up at night
These red flags matter because other conditions (celiac disease, inflammatory bowel disease, or colon cancer) can mimic IBS-C. Ruling them out is a necessary step before confirming an IBS-C diagnosis.
For the most complete care, consider working with both a gastroenterologist and a functional medicine practitioner. One rules out serious disease and manages acute symptoms; the other addresses the digestive imbalances that may be sustaining your constipation long-term.
Frequently Asked Questions
Can IBS-C go away?
IBS-C is usually a chronic, relapsing condition—not something that vanishes for good. Proper treatment can still bring long stretches of remission, and addressing root causes often delivers more durable relief than symptom management alone.
What's the best treatment for IBS-C?
There's no universal "best" treatment. Effective management usually combines diet, lifestyle changes, and medication tailored to your specific symptoms and history, ideally under professional guidance.
What should I avoid eating with IBS-C?
Common triggers include high-FODMAP foods (garlic, onion, wheat), insoluble fiber like wheat bran, caffeine, alcohol, and heavily processed foods. Triggers vary by individual, so tracking your own responses matters more than following a generic list.
What does an IBS-C flare-up feel like?
A flare typically brings bloating, cramping, a sense of incomplete evacuation, and stools that are harder or less frequent than usual. Some people also notice increased fatigue or brain fog during flares.
Can stress trigger IBS-C symptoms?
Yes. The gut-brain axis means psychological stress can directly worsen gut motility and heighten pain sensitivity, often intensifying constipation and cramping during stressful periods.
How long does it take to see improvement with IBS-C treatment?
Dietary and lifestyle changes often show results within several weeks. Root-cause work on dysbiosis or Candida overgrowth can take longer, but lasting relief is more likely once those imbalances are corrected.


